
Thirty Years in the Making: What Kerendia's Approval Means for Type 1 Diabetes and Kidney Disease
The FDA's approval of Kerendia for type 1 diabetes-associated kidney disease marks the first new treatment option in over 30 years for this underserved patient population.
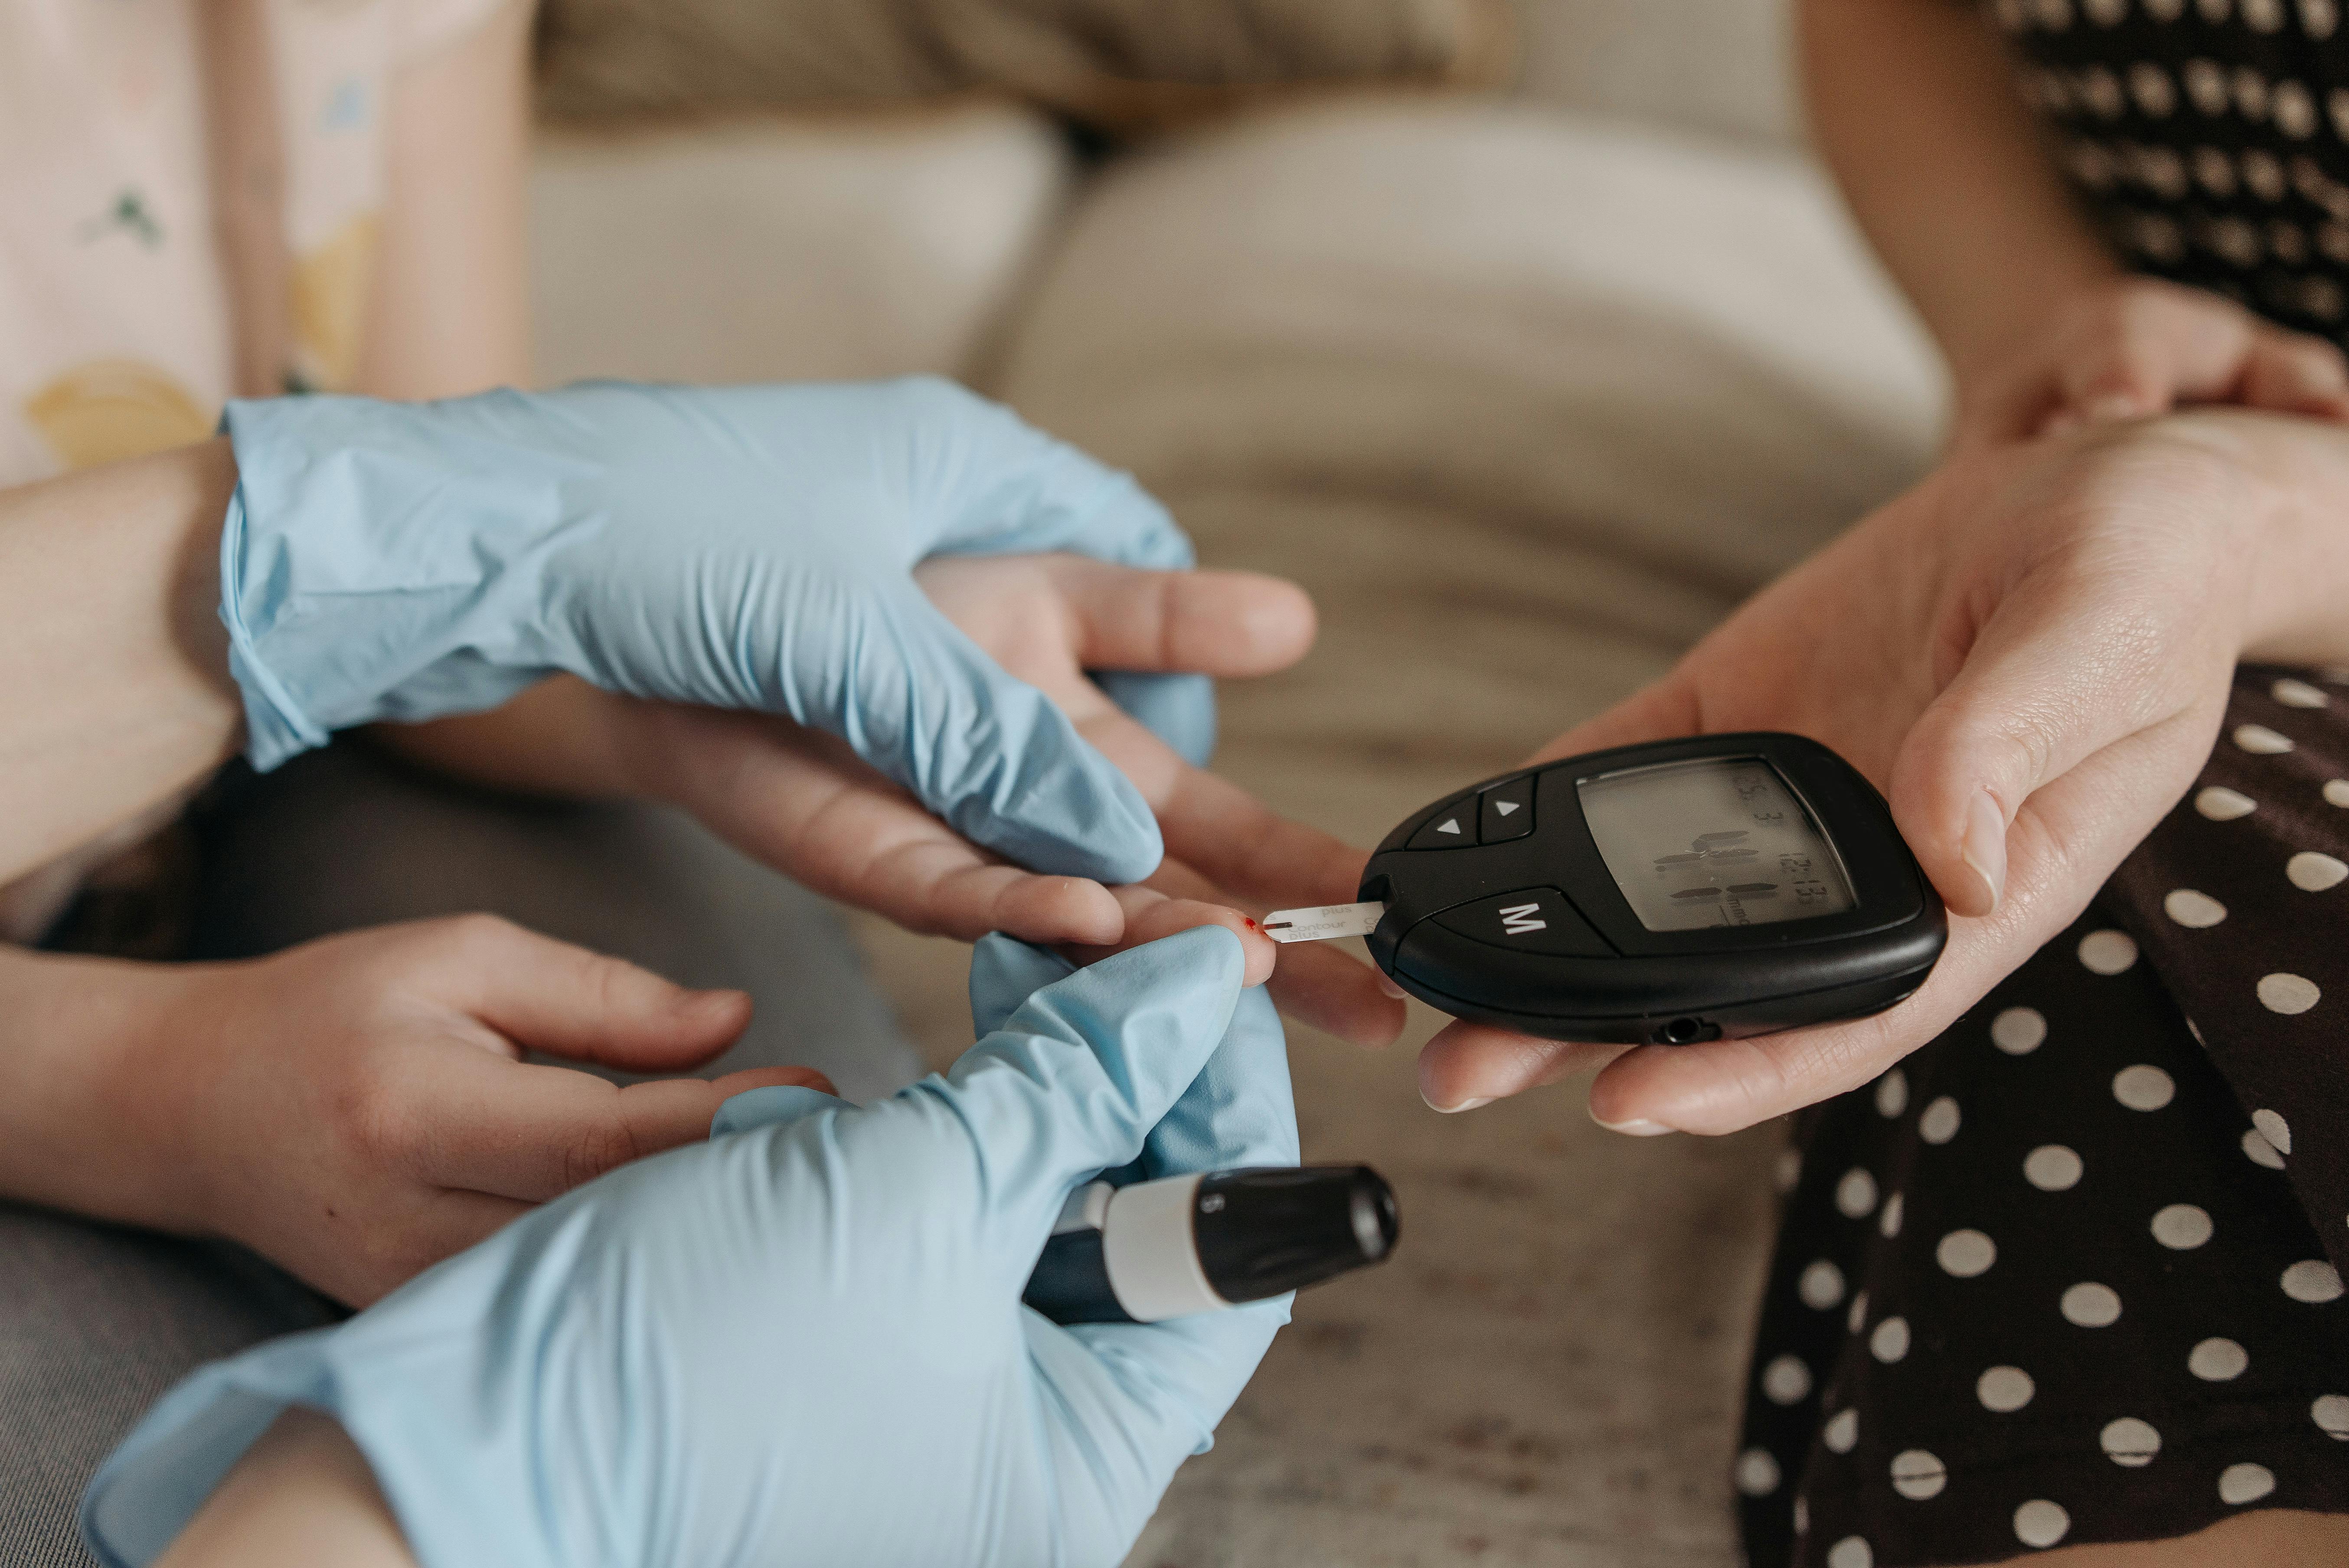
On September 17, 2026, the FDA approved Bayer's Kerendia (finerenone) for a new indication: chronic kidney disease associated with type 1 diabetes. The approval is the third indication for a drug that has quietly become one of the more consequential cardiovascular and renal medicines of the past decade. But the number that deserves the most attention is not the approval count. It is the thirty years.
For more than three decades, adults with type 1 diabetes who developed chronic kidney disease had no approved pharmacological option specifically designed to slow the progression of their kidney disease. They had blood pressure management, dietary guidance, and the same supportive measures available to patients with any form of CKD. What they did not have was a drug with a proven mechanism targeting the hormonal pathway driving their kidney damage. That gap closed last week.
Why Type 1 Diabetes and CKD Have Been Treated as an Afterthought
The neglect of CKD in type 1 diabetes is not accidental. It reflects a structural reality in pharmaceutical development: type 2 diabetes is far more prevalent, and the commercial logic of drug development has historically followed the larger patient population. Approximately 20 to 30 percent of people with type 1 diabetes in the United States develop CKD, putting them at serious risk of kidney failure, cardiovascular events, and premature death. That is a meaningful population, but it is smaller and less commercially attractive than the type 2 diabetes market, which has seen a wave of transformative approvals over the past decade.
The result has been a treatment landscape where patients with type 1 diabetes and CKD were largely managed with tools validated in type 2 populations, without the clinical trial evidence to confirm those tools worked the same way in their disease. Finerenone changes that, and the mechanism it targets is worth understanding.
What Finerenone Actually Does
Kerendia is a non-steroidal mineralocorticoid receptor antagonist. The mineralocorticoid receptor, when overactivated, drives inflammation and fibrosis in the kidneys and heart. In patients with CKD, that overactivation accelerates the scarring and functional decline that eventually leads to kidney failure. Older mineralocorticoid receptor antagonists like spironolactone and eplerenone have been available for decades, but they are steroidal compounds with significant side effect profiles, particularly around hormonal effects, that have limited their use in kidney disease populations.
Finerenone's non-steroidal structure gives it higher selectivity for the mineralocorticoid receptor and a different tissue distribution profile, with greater activity in the kidney and heart relative to the older agents. That selectivity is what allowed Bayer to build a clinical trial program across CKD and heart failure that has now produced three separate FDA approvals: CKD associated with type 2 diabetes in 2021, heart failure with preserved ejection fraction in 2025, and now CKD associated with type 1 diabetes.
The FINE-ONE Data and What They Show
The approval rests on the FINE-ONE Phase 3 trial, a randomized, double-blind, placebo-controlled study enrolling 242 adults with CKD associated with type 1 diabetes. The primary endpoint was reduction in urinary albumin-to-creatinine ratio, a key marker of kidney damage and a predictor of long-term kidney outcomes. Finerenone reduced UACR by 22 percent at three months and 28 percent at six months compared to placebo, with statistical significance at p equals 0.0001. The safety profile was consistent with what had been observed in the type 2 diabetes trials, with hyperkalemia the most notable adverse event of concern, occurring in approximately 10 percent of treated patients versus 3 percent on placebo.
The FDA approved the drug on the basis of UACR reduction as a surrogate endpoint reasonably likely to predict clinical benefit, using evidence from the FIDELIO-DKD and FIGARO-DKD trials in type 2 diabetes to bridge the kidney outcomes data to the type 1 population. That regulatory approach, extrapolating from a larger and better-characterized trial program to a smaller and harder-to-study population, is worth noting. It reflects a pragmatic recognition that conducting a full outcomes trial in a population the size of the type 1 CKD cohort would take years and might never be commercially viable. The FDA's willingness to accept that evidentiary bridge is itself a signal about how the agency is thinking about rare and underserved populations.
The Broader Implication for Underserved Populations
The Kerendia approval for type 1 diabetes CKD sits within a pattern that has been building across several therapeutic areas: the FDA using surrogate endpoints, bridging evidence, and priority review to accelerate access for patient populations that have historically been excluded from the clinical trial programs that generate the evidence base for drug approvals. The same logic has driven recent approvals in rare kidney diseases, pediatric indications, and conditions where the patient population is too small to support conventional trial designs.
What makes the Kerendia story distinctive is that type 1 diabetes CKD is not a rare disease in the traditional sense. It affects hundreds of thousands of people in the United States alone. The thirty-year gap in treatment options was not a function of scientific impossibility. It was a function of commercial prioritization. The approval does not resolve that structural problem, but it does demonstrate that a drug developed primarily for a larger indication can, with the right clinical program and regulatory strategy, be extended to a population that the market would otherwise continue to underserve.
For the patients who have been managing CKD alongside type 1 diabetes without a disease-modifying option, the approval of Kerendia is a concrete change in what their physicians can offer them. Thirty years is a long time to wait for a first. The fact that it arrived through a regulatory pathway designed to bridge evidence rather than generate it from scratch is not a limitation of the approval. It is a feature of a system learning, slowly, to reach the patients it has historically left behind.



